If a drug and its container can survive it, regulators expect the product to be sterilized in its sealed final container. Terminal sterilization delivers a validated sterility assurance level (SAL) of 10-6 or better, a safety margin that aseptic processing cannot demonstrate.
This guide shows what that means in practice for biotechs, sponsors and outsourcing teams: which methods exist, when a product qualifies, what a CDMO should prove, and how to choose a partner in 2026.
At a glance
- EU and US regulators both treat terminal sterilization as the default and aseptic processing as the justified exception.
- Steam is the preferred method. In the EU, steam cycles need an F0 of at least 8 minutes and a hold of at least 110°C.
- Ask every CDMO for cycle validation data, load patterns and annual revalidation, not just a capability slide.
- Terminal capacity is a supply chain issue too. The 2024 IV fluid shortage showed the risk of relying on one site.
What Is Terminal Sterilization?
Terminal sterilization is a validated sterilization step applied after a drug product is filled and sealed in its final container. In aseptic processing, sterility depends on keeping contamination out. In terminal sterilization, a lethal process destroys microorganisms inside the sealed unit.
The European Medicines Agency (EMA) guideline defines an SAL of 10-6 as no more than one non-sterile unit in one million. Products sterilized this way are called terminally sterilized products.
What regulators say
- EU: Finished products should be terminally sterilized in their final container whenever possible (EMA, Annex 1 paragraph 8.34).
- US: FDA’s aseptic processing guidance says aseptic processing should be used only when terminal sterilization is not feasible.
- Enforcement: A February 2026 FDA warning letter asked a contract manufacturer to assess the potential for terminal sterilization.
Terminal Sterilization vs. Aseptic Processing
For a sponsor, the choice changes the risk profile, the CDMO shortlist and the timeline.
| Factor | Terminal sterilization | Aseptic processing |
|---|---|---|
| Sterility assurance | Validated SAL of 10-6 or better that can be calculated and controlled (EMA) | No calculable SAL. Some CDMOs cite roughly 10-3 as an industry estimate (Altasciences), but regulators do not assign one |
| Where sterility is achieved | In the sealed final container | Components sterilized separately, then assembled and filled aseptically |
| Filling environment (Annex 1) | At least Grade C; Grade A with a Grade C background if the CCS identifies unusual risk (paragraphs 8.3 and 8.4) | Grade A with a Grade B background, usually inside RABS or isolators (paragraph 8.12) |
| Main validation focus | The sterilization cycle: heat penetration, biological indicators, load patterns | Aseptic process simulation, environmental monitoring, filter validation, personnel qualification |
| Product suitability | Products and containers that tolerate the cycle | Heat-, radiation- or gas-sensitive products, including most biologics |
| Regulatory position | Method of choice whenever possible | Accepted with a scientific justification (EMA guideline section 4.3) |
For the aseptic side, see PharmaSource’s guides to sterile injectable CDMOs and fill and finish.
How the Process Works
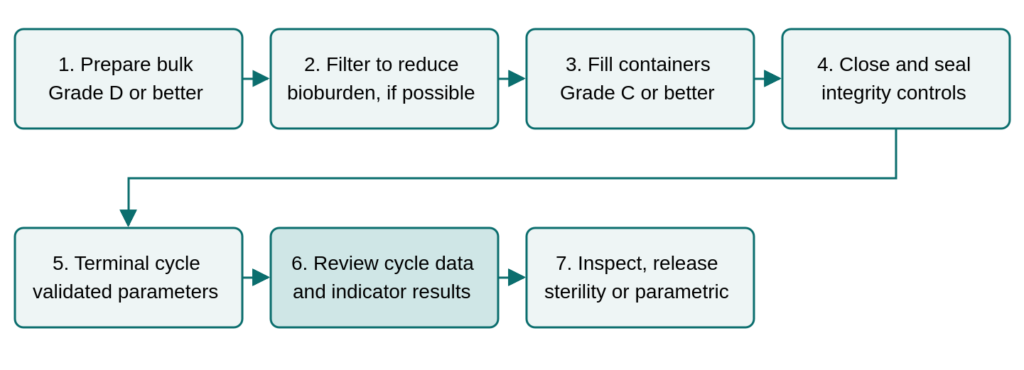
A CDMO runs a terminal process in seven steps. Annex 1 sets the cleanroom grades for the early steps.
Which Products Suit Terminal Sterilization?
- IV fluids such as saline, dextrose and lactated Ringer’s.
- Diluents, water for injection and buffers.
- Heat-stable small-molecule injectables, including analgesics and antibiotics.
- Solutions in glass vials, ampoules, plastic bags and blow-fill-seal containers.
Most monoclonal antibodies, peptides and advanced therapies cannot take the heat and are filled aseptically.
Latest Terminal Sterilization News-



Terminal Sterilization Methods at a Glance
| Method | EU reference conditions | Typical use | Watch-out |
|---|---|---|---|
| Steam | 121°C or higher for at least 15 minutes. Other cycles: F0 of at least 8 minutes, hold of at least 110°C | Aqueous solutions | Container distortion; extra data for milder cycles |
| Dry heat | 160°C or higher for at least 2 hours | Powders, oils, empty containers | Long cycles, dense loads |
| Radiation | At least 25 kGy | Heat-labile items that tolerate radiation | Radiolysis impurities; heat preferred |
| Ethylene oxide | No fixed reference | Packaging, components, devices | Last resort; residues; no parametric release |
What sponsors should know
- Steam first. The EMA says a heat-sensitive container alone is not a valid reason to skip steam. Alternative container materials should be explored first.
- Radiation is second choice. Standards were refreshed in 2025: ISO 11137-1:2025 raises energy limits, according to the International Irradiation Association. UV is not an accepted method.
- EtO is for packaging, not finished product. Annex 1 allows it only when no other method is practicable. See the EtO update below.
- VHP is mostly a device method. FDA made it an Established Category A process for devices in January 2024. That does not make it a terminal method for sealed drug products.
Is Your Product a Candidate?

Before choosing aseptic, expect regulators to ask:
- Did you try optimizing pH, excipients, container and cycle?
- Is degradation or shelf-life loss truly prohibitive? Neither is automatically a valid reason.
- Is there a documented user benefit? The EMA accepts examples such as eye drop containers.
If a full cycle is not possible, consider a post-aseptic terminal heat treatment (F0 below 8 minutes). It adds assurance but does not replace good aseptic practice.
Plan early. Carole Delauney, a sterile fill-finish expert, told PharmaSource that partners cannot select a CDMO on short notice and should pre-evaluate options 12 to 18 months ahead. Route decisions made in formulation development, covered in our formulation development guide, shape that shortlist.
What a CDMO Should Prove: Validation Checklist
Validation is where terminal sterilization succeeds or fails. Ask for evidence of:
- Bioburden limits for the bulk and every component.
- Load mapping with slowest-to-heat points and defined loading patterns.
- Three or more physical and biological runs showing SAL 10-6 or better, for cycles outside the Ph. Eur. reference.
- Hold times validated from preparation to sterilization.
- Sterile cooling media and distortion controls for plastic containers.
- Annual revalidation of worst-case heat load patterns (Annex 1 paragraph 8.39).
- Container closure integrity by validated methods.
Two common misconceptions:
- “Overkill is mandatory.” It is not. Other validated cycles are acceptable if they meet F0 of 8 minutes and bioburden expectations.
- “A low-lethality cycle still counts.” Below F0 of 8 minutes, the EMA treats the step as a post-aseptic heat treatment, not terminal sterilization.
Sterility release can sometimes rest on process data instead of a sterility test. See FDA’s parametric release guidance for moist heat. It is not accepted for gas sterilization.
Regulatory Snapshot for 2026

- EU: The revised Annex 1 has applied since August 25, 2023 (one paragraph deferred to August 2024).
- US: FDA’s core documents are older: sterilization validation (1994), aseptic processing (2004), parametric release (2010). Enforcement is still active, as the 2026 warning letter shows.
- Contract sterilization: Annex 1 expects outsourced sterilization to sit inside your contamination control strategy. A July 2026 PDA Letter article makes the same point on transport and packaging integrity.
From PharmaSource experts. Rodrigo Rial of Vivunt Pharma told PharmaSource that Annex 1 has placed a stronger focus on contamination control strategies. This is supplier commentary, best read as an industry viewpoint.
Market Size
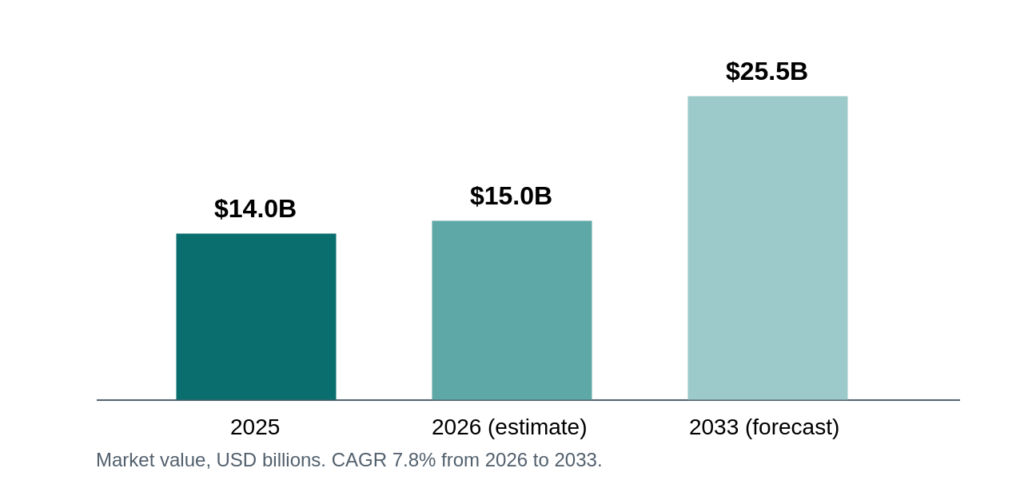
Source: Grand View Research
The global terminal sterilization services market was valued at USD 14.0 billion in 2025 and is projected to reach USD 15.0 billion in 2026 and USD 25.5 billion by 2033, growing at a CAGR of 7.8% between 2026 and 2033. North America accounted for the largest share of the market, representing 33.8% of global revenue in 2025. Market growth is primarily driven by the increasing global prevalence of healthcare-associated infections and the rising volume of surgical procedures, which continue to fuel demand for effective sterilization services.
How to Choose a Terminal Sterilization Partner
- Inspection record. Confirm GMP certification and regulatory history. The EMA expects the sterilization site to be named in the dossier, in-house or outsourced.
- Your container format. Ask about glass, plastic bags, blow-fill-seal and prefilled syringes, and distortion controls.
- Validation depth. Request load maps, indicator strategy and revalidation schedules.
- Quality system fit. Confirm how the site fits your contamination control strategy, including transport and change notification.
- Capacity and a second site. Ask about lead times and backup options. PharmaSource’s CDMO guide notes sterile fill-finish is a capacity-constrained segment.
- Method flexibility. Steam, radiation and post-aseptic heat options help if your route changes.
Key Takeaways
- Terminal sterilization gives the most measurable sterility assurance.
- Regulators expect it unless you justify otherwise.
- Steam first, radiation second, gas last for finished products.
- Validation evidence matters more than cycle severity.
- Treat contract sterilization capacity as a supply chain risk.
Frequently Asked Questions (FAQ)
What is terminal sterilization in pharma?
Sterilizing a drug product in its sealed final container with a validated process to reach an SAL of 10-6 or better.
How is it different from aseptic processing?
Aseptic processing keeps components sterile through filling. Terminal sterilization treats the sealed container, so sterility can be calculated and validated.
Which products can be terminally sterilized?
IV fluids, diluents and heat-stable small-molecule injectables. Most biologics cannot.
What is the reference steam cycle?
121°C or higher for at least 15 minutes. Other steam cycles need an F0 of at least 8 minutes and a hold of at least 110°C.
How often must cycles be revalidated?
Under Annex 1, at least annually for worst-case heat load patterns.
Is ethylene oxide still used?
Yes, mainly for packaging and devices. EU guidance allows it for products only when nothing else works, and US emission rules are under reconsideration in 2026.